I’ve written here about my ideas page of economics papers I’d like to see.
After that post I heard from others who maintain similar pages. David Friedman has a small page here with research ideas, along with larger pages of short story ideas and product ideas.
HiveReview is a site where one can post or comment on both completed papers and paper ideas. The site does many things at once, but one use case is to post ideas in search of collaborators or to search for projects where someone wants a collaborator for their idea.
I learned today that Gwern Branwen maintains a large page of “Questions“, some of which could be research ideas, mostly outside of economics. He also has pages of research ideas and startup ideas. Some examples of Questions:
Given the crucial role of trust and shared interests in success stories like Xerox PARC or the Apollo Project or creative collaborations in general, why are there so few extremely successful pairs of identical twins?
Nicotine alternatives or analogues: there seem to be none, but why not?
Nicotine is one of the best stimulants on the market: legal, cheap, effective, relatively safe, with a half-life less than 6 hours. It also affects one of the most important and well-studied receptors. Why are there no attempts to develop analogues or replacements for nicotine which improve on it eg. by making it somewhat longer-lasting or less blood-pressure-raising, when there are so many variants on other stimulants like amphetamines or modafinil or caffeine?
Medicaid is a health insurance program for those with low incomes, funded largely by states. Overall it accounts for less than 20% of US medical spending. But there is one area where it is the dominant payer: nursing homes. Nursing homes are expensive, and Medicare (the typical insurance for those over 65) won’t cover them after the first hundred days, so most nursing home residents end up paying out of pocket until they burn through all their savings and wind up on Medicaid. At which point, Medicaid pays about $100,000 per year to the nursing home for the rest of their life.
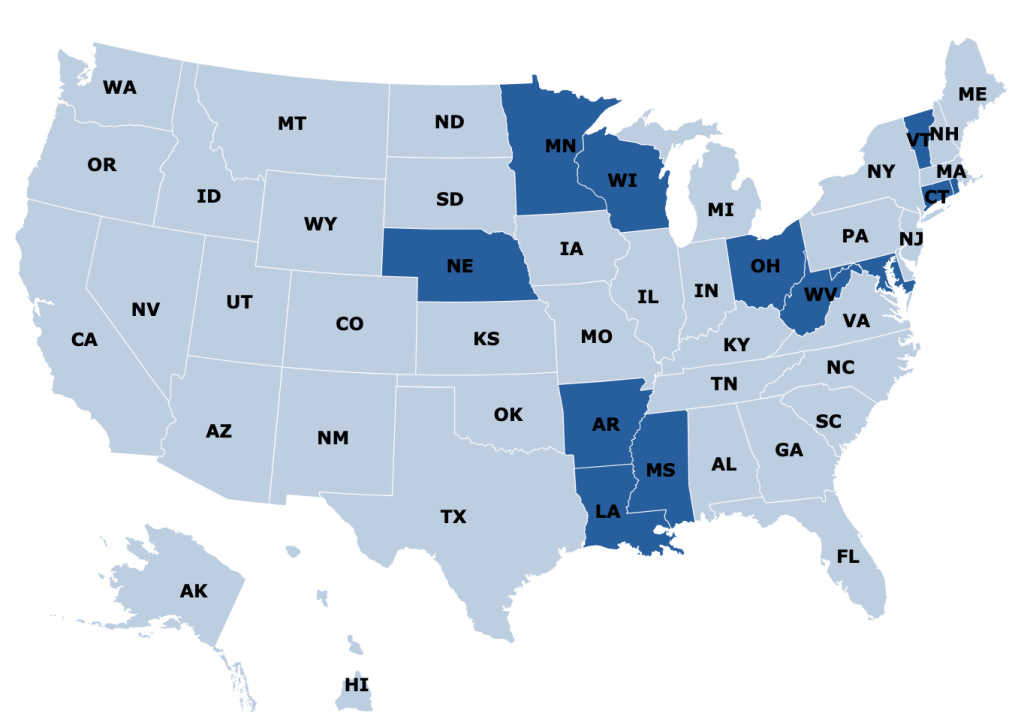
States are responsible for up to half of that cost, and so start looking for ways to save money. One idea they have is to make it harder to build nursing homes: if there aren’t beds available, potential nursing home patients will have to stay home instead, where they can’t rack up Medicaid spending the same way. In fact, some states go all the way to a complete moratorium on new nursing homes:
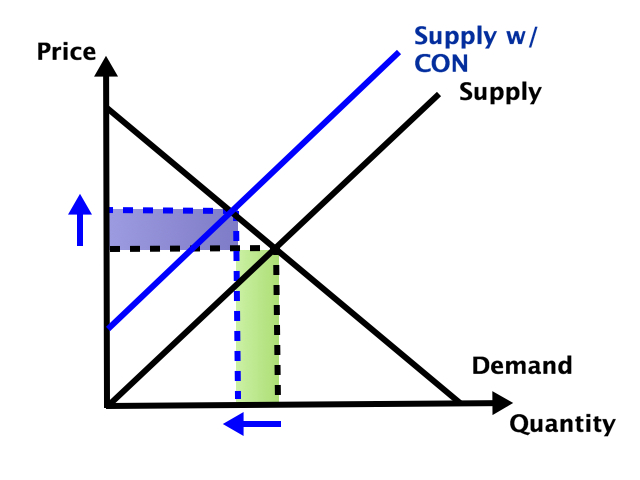
Some other states allow new nursing homes, but only with a special permission slip called a Certificate of Need (CON). CON is often required for other types of health facilities as well, like hospitals or dialysis centers. Research by me and others has generally found that CON doesn’t work as a way to reduce spending, and in fact actually increases it. CON might reduce the number of facilities, but that reduction of supply and competition gives the remaining facilities more power to raise prices.
So which effect dominates- does the smaller number of facilities reduce total spending, or do the higher prices increase it? It depends on the elasticity of demand:
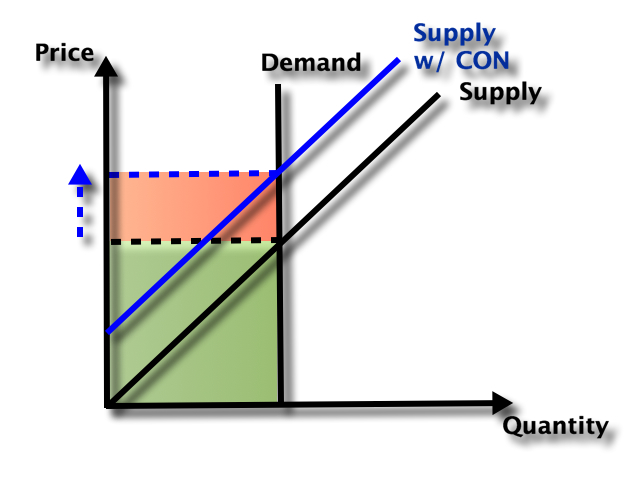
In health care demand is typically quite inelastic, so the price effect dominates, and spending goes up:
But nursing homes could be an exception here. Elasticity of demand could be relatively high because of the number of potential substitutes- home care or assisted living for those with relatively low medical needs, hospitals for those with relatively high medical needs. Plus this is the one type of health care where Medicaid is the dominant payer. They could be especially resistant to price increases here, both due to their market power and their willingness to keep prices so low that facilities won’t take Medicaid patients (another way to save money!).
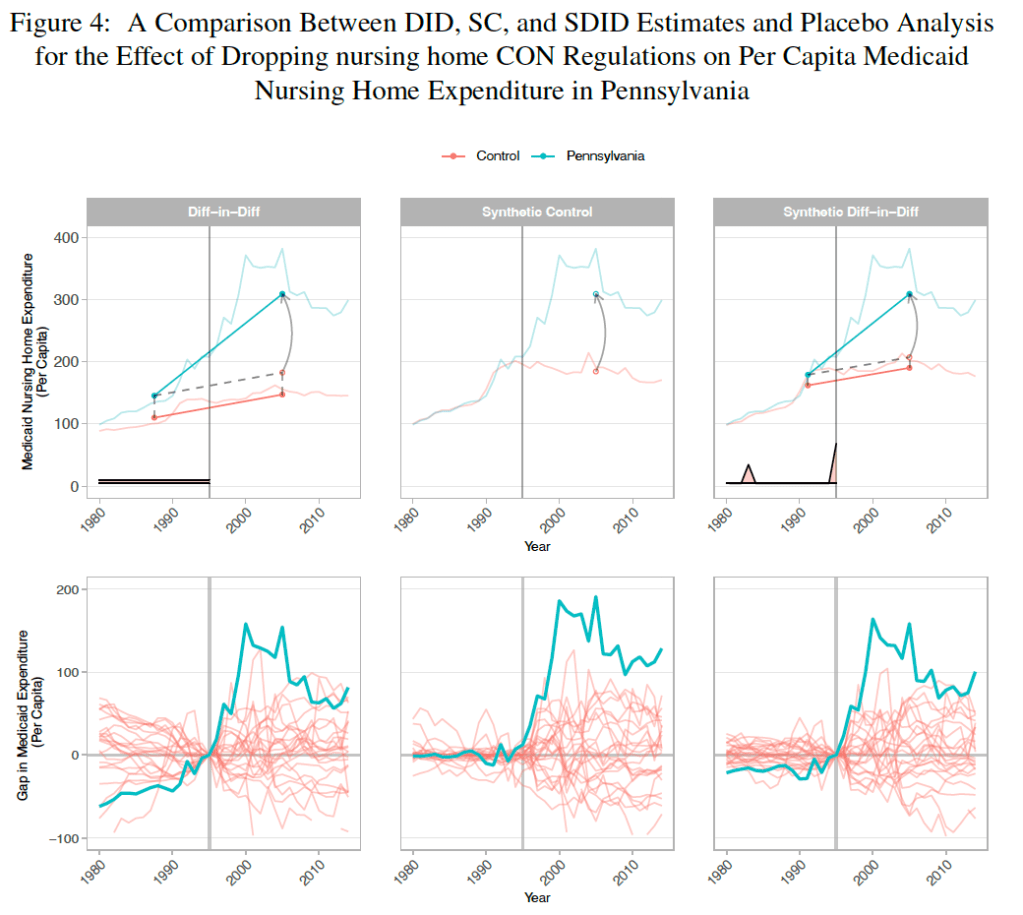
A new paper by Vitor Melo and Elijah Neilson finds that this is indeed the case. Indiana, Pennsylvania, and North Dakota repealed their nursing home CON requirements in the ’90s, and at least for IN and PA their Medicaid spending went way up. The paper uses a new “synthetic difference in difference” technique that seems appropriate, and creates figures that seem confusing at first but get a ton of information across:
They correctly note that they don’t evaluate the welfare effects of the policy; it’s possible that the extra nursing home beds following CON repeal bring huge benefits to seniors that are worth the higher spending. But nursing homes could be the exception to the general rule that CON fails to achieve the goals, like reduced spending, that advocates set for it.
West Virginia just repealed their Certificate of Need requirement for hospitals and birthing centers. Until now anyone wanting to open or expand a hospital needed to apply to a state board for permission. The process took time and money and could result in the board saying “no thanks, we don’t think the state needs another hospital”.
Now anyone wanting to open or expand a hospital and birthing center can skip this step and get to work. This means more facilities and more competition, which in turn leads to lower health care spending relative to trend.
Of course, the rest of West Virginia’s Certificate of Need requirements remain in place; if you want to open many other type of health care facilities, or purchase major equipment like an MRI, you must still get the state board to approve its “necessity”. In some cases, you shouldn’t even bother applying; West Virginia has a Moratorium on opioid treatment programs. Ideally West Virginia would join its neighbor Pennsylvania in a complete repeal of Certificate of Need requirements.
But making it easier to build hospitals and birthing centers is a major step. Hospitals are the largest single component of health spending in the US, and improved facilities might help reduce West Virginia’s infant mortality from its current level as the 4th worst state.
Update 4/7/23: A knowledgable correspondent suggests that the law may only allow existing hospitals to expand without CON (while totally new hospitals would still require one), citing this article. The text of the bill itself seems ambiguous to me. The section “Exemptions from certificate of need” adds “Hospital services performed at a hospital”. For birthing centers by contrast, new construction is clearly now allowed by right: exemptions from CON now include “Constructing, developing, acquiring, or establishing a birthing center”.
Partly this has been a regulatory issue. Raising equity adds all sorts of legal burdens. Traditionally businesses could only accept equity investments from accredited investors and a small number of friends and family unless they did a full IPO and became public (hard enough that there are less that 5000 public companies in the US out of millions of businesses). This changed with the JOBS Act of 2012, which allowed small businesses to raise money from large numbers of non-accredited investors without having to register with the SEC.
Following the JOBS Act, equity crowdfunding sites like WeFunder emerged to match new businesses with potential investors. But equity crowdfunding has taken off relatively slowly:
Its seen more success recently with some additional regulatory relief and the overall market boom of 2020-2021. But at ~$400 million/yr, its still well under 1% of all venture investment (~$300 billon/yr), which is itself tiny relative to the public stock market ($40 trillion market cap).
Why has equity crowdfunding been slow to take off? Partly its new and most people still don’t know about it. Partly early-stage companies aren’t a good way for most people to invest a significant fraction of their money; you probably want to be at least close to accredited investor levels (~$300k/yr income or $1 million liquid wealth) for it to make sense, and those at the accredited investor level already have other options. WeFunder is up front about the risks:
The other issue here is with asymmetric information and adverse selection. Its hard to find out much information about early-stage companies to know if they are a good investment; part of the point of the JOBS Act is that the companies don’t need to tell you much. The companies themselves have a better idea of how well they are doing, and the best ones might not bother with equity crowdfunding; they could probably raise more money with less hassle by going to venture funds or accredited angel investors.
I’ve long thought this adverse selection would be the killer issue, but my impression (not particularly well-informed and definitely not investment advice) is that there are now quality companies raising money this way, or at least companies that could easily raise money elsewhere. WeFunder has a whole page of Y-Combinator-backed companies raising money there. This week Substack, an established company that has already raised lots of venture funding, offered crowd equity and reached the $5 million limit of how much they could legally accept in a single day.
Overall I think this model is working well enough that I’m no longer in a hurry to become an accredited investor. Accredited investors have many more options for companies they can invest in and aren’t subject to the $2,200/yr limit on how much they can invest in early-stage companies. But even if I completed the backdoor process of getting accredited without being rich, I wouldn’t want to put more than $2,200/yr into early-stage companies until I was a millionaire, at which point I’d be accredited the usual way. And while most companies aren’t raising crowd equity, enough are that there seem to me to be no shortage of choices.
I recently bought a used desktop computer for what seemed like next to nothing. $240 for a machine more powerful than my much-more-expensive 2019 MacBook Pro, most notably due to its 32GB of RAM. Desktops have always been cheaper than equivalently powerful laptops, Windows computers cheaper than Macs, and used computers cheaper than new, so this isn’t totally shocking. But the extent of the difference still surprised me. For instance, buying a new desktop from Dell with similar specs to the used one I just got would cost $1399.
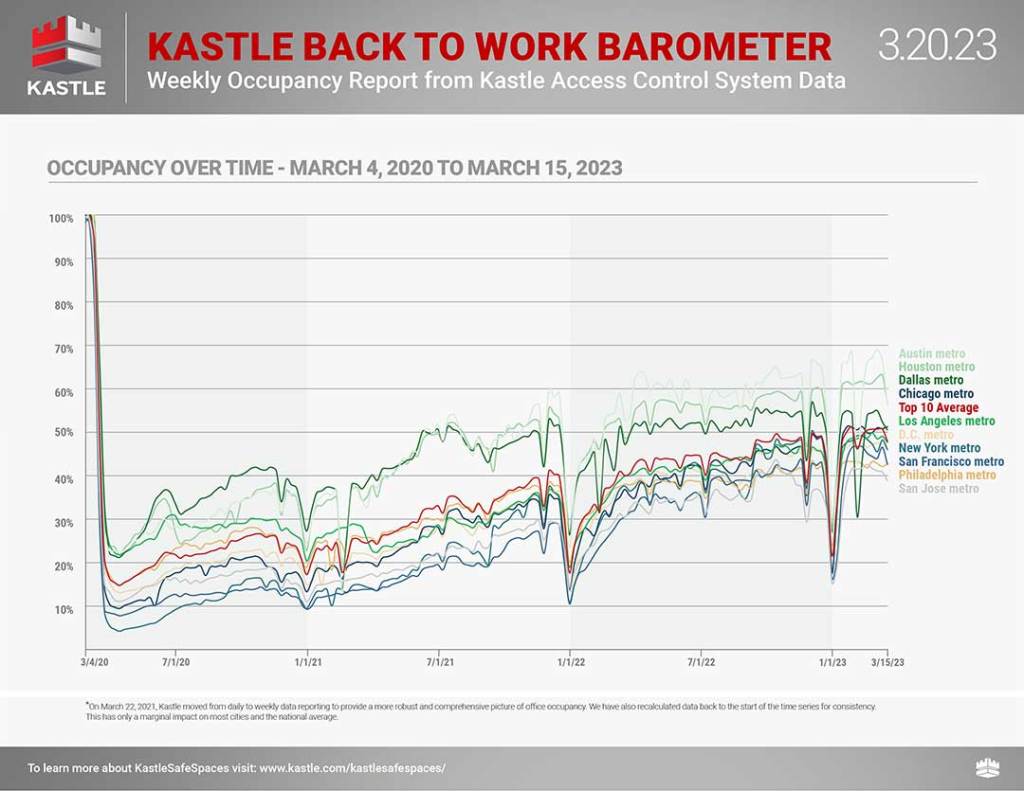
So why is the used discount so big right now? My guess is that its one more knock-on effect of work-from-home. Remote work has been the most persistent change from Covid, and there’s been a huge decline in the demand for office space, with occupancy rates still half of pre-Covid levels.
This means that offices are on sale relative to their pre-Covid prices. Office REITs are down 37% over the past year even after the Covid-induced drop of the previous two years. So it makes sense that all sorts of office equipment is on sale too. Offices tend to be full of employer-owned desktop computers, but when employees work from home they typically use their own machine or a company laptop. That means less demand for office desktops going forward, and a big overhang of existing office desktops that are being under-used. Employers realizing this may just sell them off cheap. Several things about the refurbished desktop I bought, such as its Windows Pro software, indicate that it used to be in an office.
It covers the years 1990 to 2019 for every US state, and has life expectancy at birth, age 25, and age 65. It includes breakdowns by sex and by race and ethnicity, though the race and ethnicity breakdowns aren’t available for every state and year.
This is one of those things that you’d think would be easy to find elsewhere, but isn’t. The CDC’s National Center for Health Statistics publishes state life expectancy data, but only makes it easily available back to 2018. The United States Mortality DataBase has state life expectancy data back to 1959, but makes it quite hard to use: it requires creating an account, uses opaque variable names, and puts the data for each state into a different spreadsheet, requiring users who want a state panel to merge 50 sheets. It also bans re-sharing the data, which is why the dataset I present here is based on IHME’s data instead.
The IHME data is much more user-friendly than the CDC or USMDB, but still has major issues. By including lots of extraneous information and arranging the data in an odd way, it has over 600,000 rows of data; covering 50 states over 30 years should only take about 1,500 rows, which is what I’ve cleaned and rearranged it to. IHME also never actually gives the most basic variable: life expectancy at birth by state. They only ever give separate life expectancies for men and women. I created overall life expectancy by state by averaging life expectancy for men and women. This gives people any easy number to use, but a simple average is not the ideal way to do this, since state populations aren’t exactly 50/50, particularly for 65 year olds. If you’re doing serious work on 65yo life expectancy you probably want to find a better way to do this, or just use the separate male/female variables. You might also consider sticking with the original IHME data (if its important to have population and all cause mortality by age, which I deleted as extraneous) or the United States Mortality DataBase (if you want pre-1990 data).
Overall though, my state life expectancy panel should provide a quick and easy option that works well for most people.
Here’s an example of what can be done with the data:
If states are on the red line, their life expectancy didn’t change from 1990 to 2019. If a state were below the red line, it would mean their life expectancy fell, which done did (some state names spill over the line, but the true data point is at the start of the name). The higher above the line a state is, the more the life expectancy increased from 1990 to 2019. So Oklahoma, Mississippi, West Virginia, Kentucky and North Dakota barely improved, gaining less than 1.5 years. On the other extreme Alaska, California, New York improved by more than 5 years; the biggest improvement was in DC, which gained a whopping 9.1 years of life expectancy over 30 years. My initial thought was that this was mainly driven by the changing racial composition of DC, but in fact it appears that the gains were broad based: black life expectancy rose from 65 to 72, while white life expectancy rose from 77 to 87.
That’s the title of a blockbuster new paper by Shikhar Singla. The headline finding is that increased regulatory costs are responsible for over 30% of the increase in market power in the US since the 1990’s. That’s a big deal, but not what I found most interesting.
One big advance is simply the data on regulation. If you want to measure the effect of regulation on different industries, you need to come up with a way to measure how regulated they are. The crude, simple old approach is to count how many pages of regulation apply to a broad industry. The big advance of Mercatus’ RegData was to use machine learning to identify which specific industry is being discussed near “restrictive words” in the Code of Federal Regulation that indicate a regulatory restriction is being imposed. But not all regulatory words (even restrictive ones) are created equal; some impose very costly restrictions, most impose less costly restrictions, and some are even deregulatory. Singla’s solution is to take the government’s estimates of regulatory costs and apply machine learning there:
This paper uses machine learning on regulatory documents to construct a novel dataset on compliance costs to examine the effect of regulations on market power. The dataset is comprehensive and consists of all significant regulations at the 6-digit NAICS level from 1970-2018. We find that regulatory costs have increased by $1 trillion during this period.
The government’s estimates of the costs are of course imperfect, but almost certainly add information over a word-count based approach. Both approaches agree that regulation has increased dramatically over time. How does this affect businesses? Here’s what’s highlighted in the abstract:
We document that an increase in regulatory costs results in lower (higher) sales, employment, markups, and profitability for small (large) firms. Regulation driven increase in con- centration is associated with lower elasticity of entry with respect to Tobin’s Q, lower productivity and investment after the late 1990s. We estimate that increased regulations can explain 31-37% of the rise in market power. Finally, we uncover the political economy of rulemaking. While large firms are opposed to regulations in general, they push for the passage of regulations that have an adverse impact on small firms
More from the paper:
an average small firm faces an average of $9,093 per employee in our sample period compared to $5,246 for a large firm
a 100% increase in regulatory costs leads to a 1.2%, 1.4% and 1.9% increase in the number of establishments, employees and wages, respectively, for large firms, whereas it leads to 1.4%, 1.5% and 1.6% decrease in the number of establishments, employees and wages, respectively for small firms when compared within the state-industry-time groups. Results on employees and wages provide evidence that an increase in regulatory costs creates a competitive advantage for large firms. Large firms get larger and small firms get smaller.
The fact that large firms benefit while small firms are harmed is what drives the increase in concentration and market power.
What I like and dislike most about this paper is the same thing: its a much better version of what Diana Thomas and I tried to do in our 2017 Journal of Regulatory Economics paper. We used RegData restriction counts to measure how regulation affected the number of establishments and employees by industry, and how this differed by firm size. I wish I had thought of using published regulatory cost measures like Singla does, but realistically even if I had the idea I wouldn’t have had the machine learning chops to execute it. The push to quantify what “micro” estimates mean for economy-wide measures is also excellent. I hope and expect to see this published soon in a top-5 economics journal.
Thinking about one of my older papers today, since I just heard it won the Eckstein award for best paper in the Eastern Economic Journal in 2019 & 2020.
One big selling point of the Affordable Care Act was that by offering more non-employer-based options for health insurance, it would free people who felt locked into their jobs by the need for insurance. This would free people up to leave their jobs and do other things like start their own businesses. Did the ACA actually live up to this promise?
It did, at least for some people. The challenge when it comes to measuring the effect of the ACA is that it potentially affected everyone nationwide. If entrepreneurship rises following the implementation of the ACA in 2014, is it because of the ACA? Or just the general economic recovery? Ideally we want some sort of comparison group unaffected by the ACA. If that doesn’t really exist, we can use a comparison group that is less affected by it.
That’s what I did in a 2017 paper focused on younger adults. I compared those under age 26 (who benefit from the ACA’s dependent coverage mandate) to those just over age 26 (who don’t), but found no overall difference in how their self-employment rates changed following the ACA.
In the 2019 Eastern Economic Journal paper, Dhaval Dave and I instead consider the effect of the ACA on older adults. We compare entrepreneurship rates for people in their early 60’s (who might benefit from the availability of individual insurance through the ACA) with a “control group” of people in their late 60’s (who are eligible for Medicare and presumably less affected by the ACA). We find that the ACA led to a 3-4% increase in self-employment for people in their early 60’s.
Figure 1 from our 2019 EEJ paper
Why the big difference in findings across papers? My guess is that it’s about age, and what age means for health and health insurance. People in their 60s are old enough to have substantial average health costs and health insurance premiums, so they will factor health insurance into their decisions more strongly than younger people. In addition, the community rating provisions of the ACA generally reduced individual premiums for older people while raising them for younger people.
In sum, the ACA does seem to encourage entrepreneurship at least among older adults. At the same time, our other research finds that the employer-based health insurance system still leads Americans to stay in their jobs longer than they would otherwise choose to.
The US government is great at collecting data, but not so good at sharing it in easy-to-use ways. When people try to access these datasets they either get discouraged and give up, or spend hours getting the data into a usable form. One of the crazy things about this is all the duplicated effort- hundreds of people might end up spending hours cleaning the data in mostly the same way. Ideally the government would just post a better version of the data on their official page. But barring that, researchers and other “data heroes” can provide a huge public service by publicly posting datasets that they have already cleaned up- and some have done so.
That’s what I said in December when I added a data page to my website that highlights some of these “most improved datasets”. Now I’m adding the Behavioral Risk Factor Surveillance Survey. The BRFSS has been collected by the Centers for Disease Control since the 1980s. It now surveys 400,000 Americans each year on health-related topics including alcohol and drug use, health status, chronic disease, health care use, height and weight, diet, and exercise, along with demographics and geography. It’s a great survey that is underused because the CDC only offers it in XPT and ASC formats. So I offer it in Stata DTA and Excel CSV formats here.
Let me know what dataset you’d like to see improved next.
The key lesson, the thing I would impart to any aspiring bloggers, content creators, or newsletter proprietors, is that the cornerstone of internet success is not intelligence or novelty or outrageousness or even speed, but regularity. There are all kinds of things you can do to develop and retain an audience — break news, loudly talk about your own independence, make your Twitter avatar a photo of a cute girl — but the single most important thing you can do is post regularly and never stop.
Granted, “work hard and keep doing the thing you’re doing” is probably above-replacement advice for any kind of entrepreneurial activity. But it’s particularly true for online content creation. As Yglesias suggests, the internet and feed-based social platforms have constructed an insatiable demand for content, so if you can produce content mechanically, without requiring expensive resources (such as time, wit, or subject-specific knowledge), you’re in an excellent position to take advantage. But most importantly, this demand is so insatiable that there is currently no real economic punishment for content overproduction. You will almost never lose money, followers, attention, or reach simply from posting too much.
That is from an excellent post by Max Read. It is fairly short and has some good examples, so I recommend reading the whole thing. Tyler Cowen made a similar point back in 2019:
There’s a certain way in which on the internet you can’t be overexposed. There’s just a steady stream of you, it feels like being overexposed compared to the standards of 1987 or whenever, but in fact it’s not and people are picking and choosing. And you end up just dominating a particular space in a particular kind of way. And I think most older people have not made that transition mentally to understanding how you should exist intellectually on the internet.
Of course, this is also part of Joy’s idea with this site and why we write every day:
It’s just time to start writing more. This is a model that I have learned from Tyler Cowen, and most writers I admire write every day whether or not they have time for it. David Perell has tweeted that writing and thinking are the same thing. Thus, if you are a thinker, writing is not a waste of time. Writing is the thing you are doing anyway in your muddled head.